Systemic Enamel Hypoplasia: Etiology, Classification, Clinical Presentation, and Treatment
Developmental Enamel Defects: Systemic Hypoplasia. Overview of the Etiology, Clinical Forms, Diagnosis, and Aesthetic Restoration Techniques for Teeth.


Anesthesia
Pain management and sedation techniques

Angiology
Arterial and venous pathologies

Cardiology
Acquired and congenital heart diseases

Dentistry
Diseases of teeth, gums, and the oral cavity

Dermatology
Disorders of the skin and subcutaneous tissue

Embryology
Stages of embryogenesis and congenital anomalies

Endocrinology
Disorders of the glands and hormonal imbalance

Gastroenterology
Stomach, intestinal, and digestive diseases

Gynecology
Diseases of female reproductive organs

Hematology
Hematopoiesis and blood-related disorders

Hepatology
Liver, gallbladder, and biliary tract diseases

Histology
Microscopic tissue and cell structures

Infectious diseases
Bacterial, viral, and parasitic infections

Neurology
Brain, spinal cord, and peripheral nerve disorders

Obstetrics
Pregnancy complications and abnormal fetal positions

Oncology
Cancer types, benign and malignant tumors

Ophthalmology
Conditions affecting the eyes and vision

Orthopedics
Bone, joint, and soft tissue disorders

Otorhinolaryngology
Ear, nose, and throat diseases

Pediatrics
Child health, development, and clinical conditions

Physiology
Biological processes within organs and systems

Plastic surgery
Reconstructive and aesthetic procedures

Pulmonology
Lung and respiratory tract diseases

Traumatology
Acute injuries and musculoskeletal trauma

Urology
Urinary tract and male reproductive disorders
Anesthesia
Pain management and sedation techniques
Angiology
Arterial and venous pathologies
Cardiology
Acquired and congenital heart diseases
Dentistry
Diseases of teeth, gums, and the oral cavity
Dermatology
Disorders of the skin and subcutaneous tissue
Embryology
Stages of embryogenesis and congenital anomalies
Endocrinology
Disorders of the glands and hormonal imbalance
Gastroenterology
Stomach, intestinal, and digestive diseases
Gynecology
Diseases of female reproductive organs
Hematology
Hematopoiesis and blood-related disorders
Hepatology
Liver, gallbladder, and biliary tract diseases
Histology
Microscopic tissue and cell structures
Infectious diseases
Bacterial, viral, and parasitic infections
Neurology
Brain, spinal cord, and peripheral nerve disorders
Obstetrics
Pregnancy complications and abnormal fetal positions
Oncology
Cancer types, benign and malignant tumors
Ophthalmology
Conditions affecting the eyes and vision
Orthopedics
Bone, joint, and soft tissue disorders
Otorhinolaryngology
Ear, nose, and throat diseases
Pediatrics
Child health, development, and clinical conditions
Physiology
Biological processes within organs and systems
Plastic surgery
Reconstructive and aesthetic procedures
Pulmonology
Lung and respiratory tract diseases
Traumatology
Acute injuries and musculoskeletal trauma
Urology
Urinary tract and male reproductive disorders
Specialties
AnesthesiaAngiologyCardiologyDentistryDermatologyEmbryologyEndocrinologyGastroenterologyGynecologyHematologyHepatologyHistologyInfectious diseasesNeurologyObstetricsOncologyOphthalmologyOrthopedicsOtorhinolaryngologyPediatricsPhysiologyPlastic surgeryPulmonologyTraumatologyUrology
This article is for informational purposes only
The content on this website, including text, graphics, and other materials, is provided for informational purposes only. It is not intended as advice or guidance. Regarding your specific medical condition or treatment, please consult your healthcare provider.
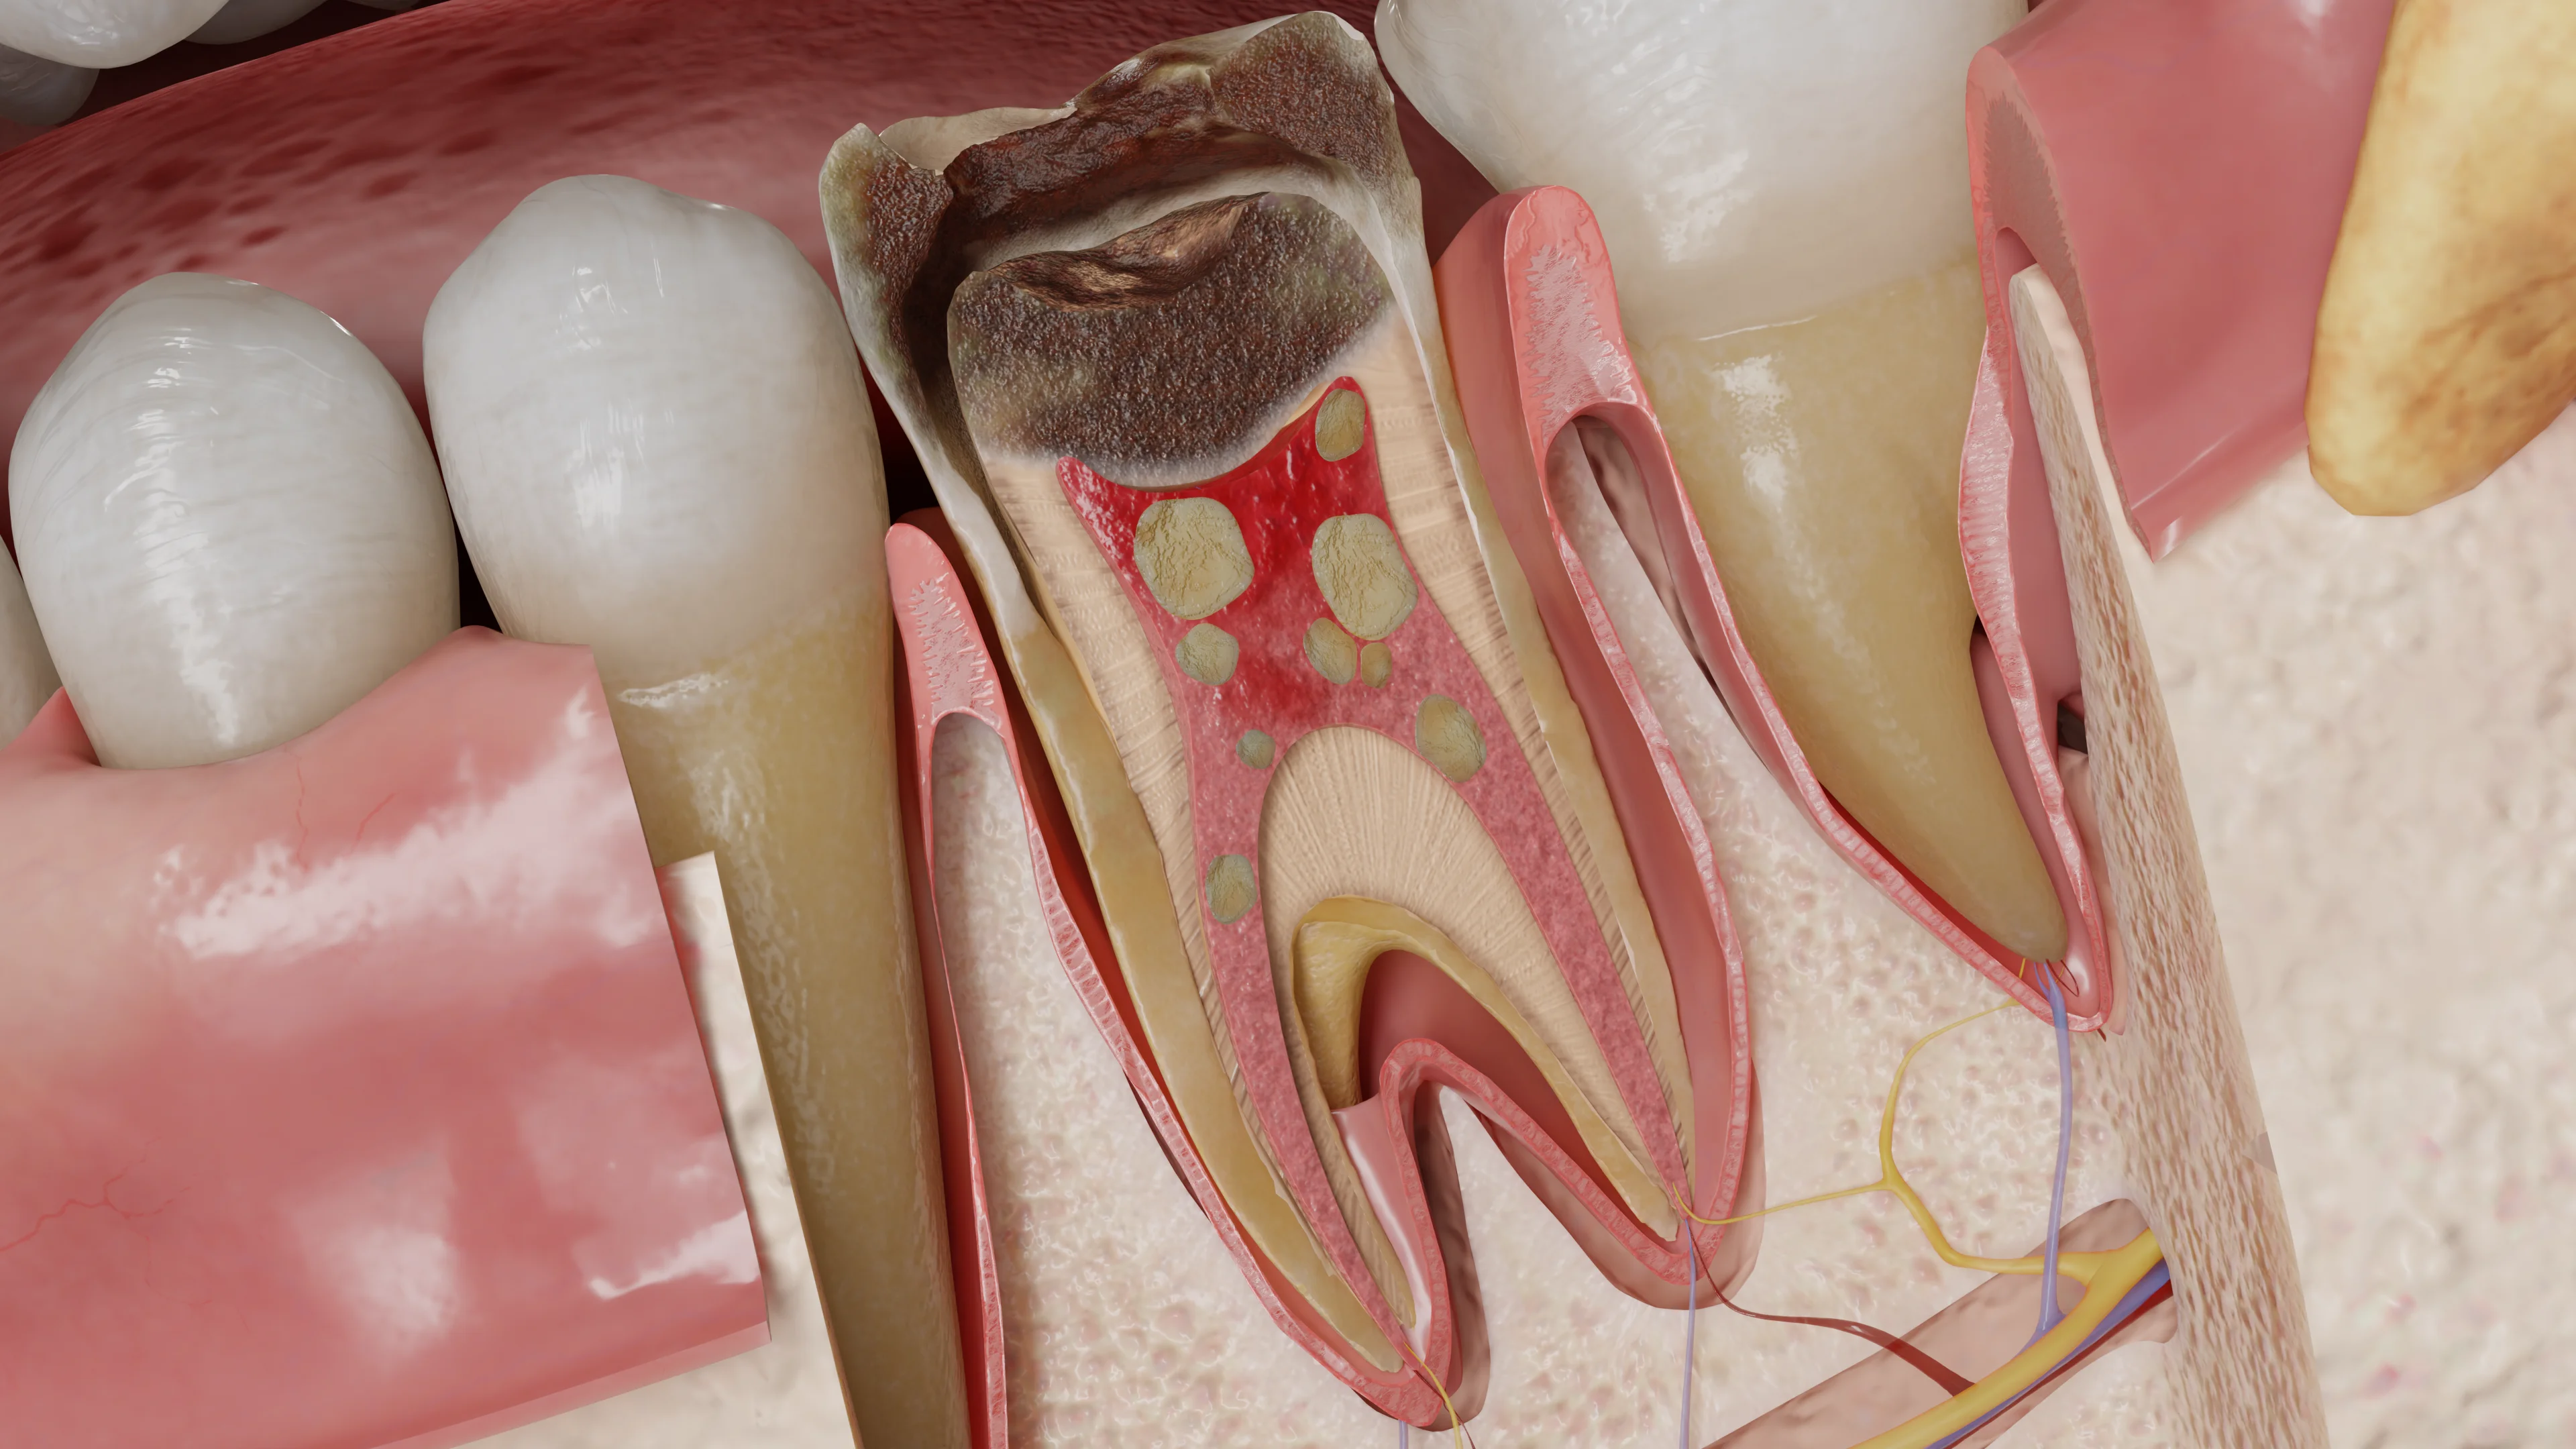
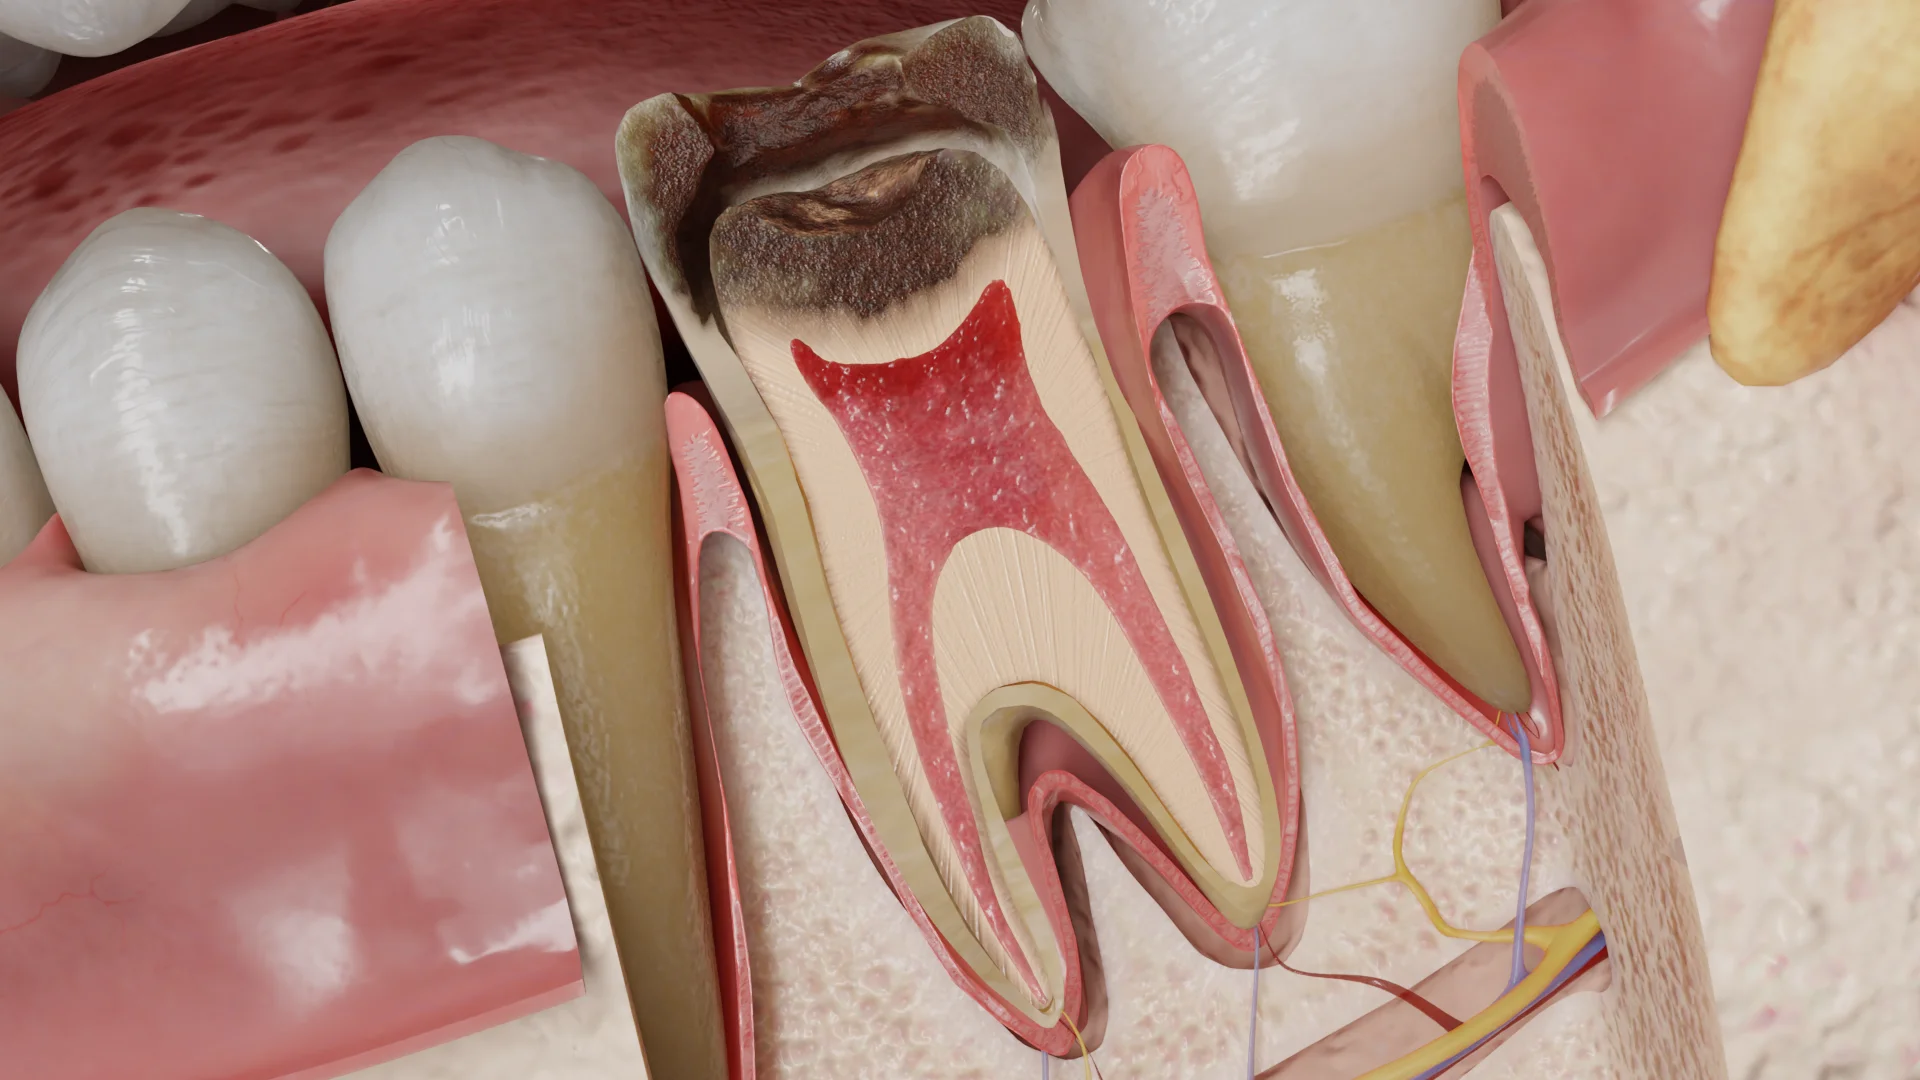
Irreversible pulpitis is an inflammation of the dental pulp that persists even after the causative factor is eliminated.
The main cause of pulpitis development is the penetration of the carious process into the pulp. It can also be caused by tooth trauma (mechanical injury, occlusal trauma, orthodontic tooth movement), iatrogenic factors (preparation without cooling, poor isolation of the working field, accidental pulp exposure, use of toxic lining and restorative materials).
During microbial invasion of the pulp, inflammatory defense mechanisms are activated, neutrophils accumulate, and immune cells gather. Neutrophils migrate from the pulp to the adjacent openings of dentinal tubules and release oxygen radicals, lysosomal enzymes, and nitric oxide, contributing to tissue destruction. The release of pro-inflammatory neuropeptides causes vasodilation and increased permeability of vessel walls which cumulatively contribute to tissue destruction.
The exudate is initially serous, then sero-purulent and purulent. Pressure increases in the tissues, and a pulp necrosis focus develops. This results in increased pressure within the tissues and a necrotic focus in the pulp. In the surrounding tissues, a picture of chronic inflammation is observed: macrophages, fibroblasts, mast cells, and foam cells. Even a limited necrosis zone is a sign of reversible pulpitis transitioning to irreversible. The initial necrosis area slowly spreads deeper in the apical direction.
As the inflammation progresses, purulent liquefaction and necrosis of the pulp may develop. However, if the exudate drains spontaneously, the acute process can shift to a chronic state.
In chronic pulpitis, proliferative changes are dominant: inflammatory edema disappears, and fibrous elements grow extensively.
Inflammatory mediators, such as bradykinin and histamine, activate C-type nerve fibers. C-fibers are unmyelinated fibers that have slower conduction velocities, a smaller diameter, and a higher threshold of excitation compared to A𝛅 fibers. They are located deeper within the tissue and are primarily activated by heat, causing dull, aching, persistent, and sometimes diffuse pain. Cold exposure in patients with symptomatic irreversible pulpitis can cause vasoconstriction and a drop in pulp pressure, which may provide temporary pain relief. C-fibers also differ from A fibers in their ability to maintain functional integrity during tissue hypoxia and continue to function for a longer time as inflammation progresses. The reaction of C-fibers indicates that pulp damage is irreversible.
Depending on the etiologic factor, the affected tooth may exhibit:
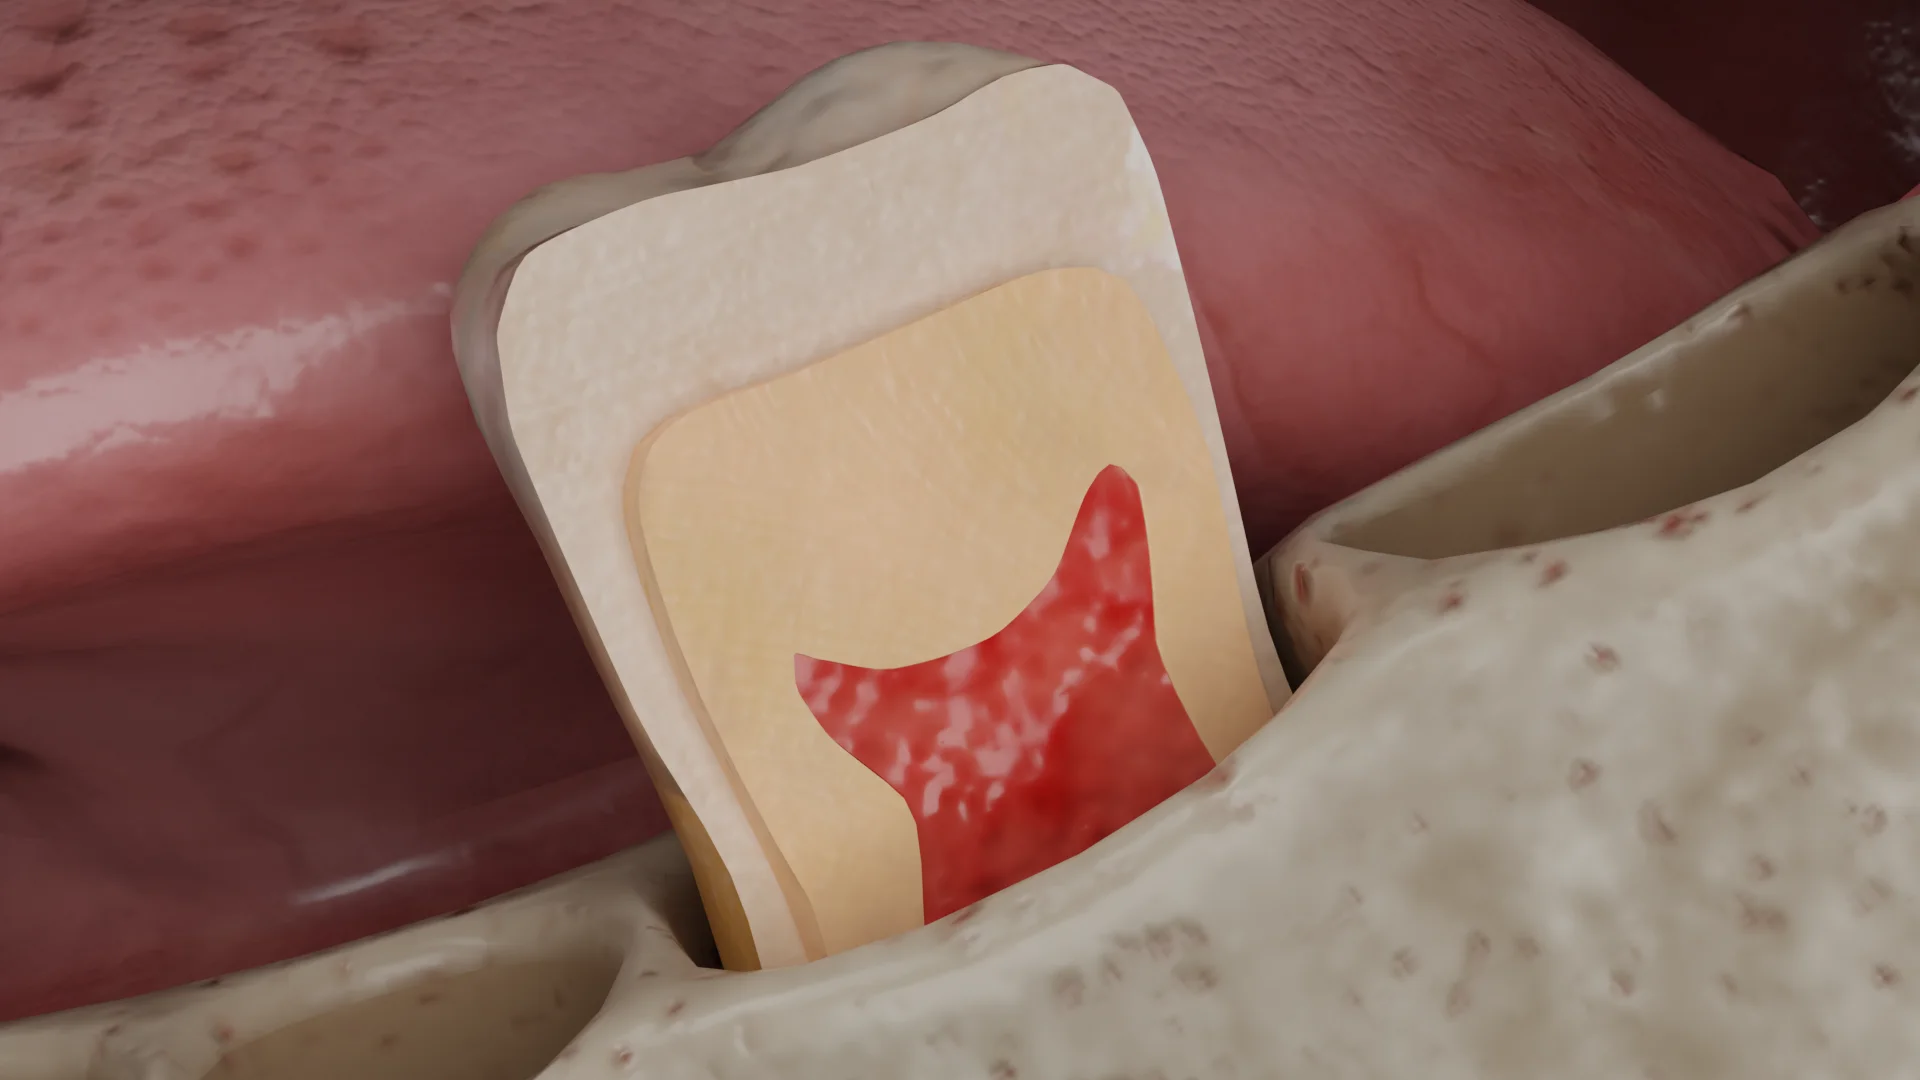
In an acute process, the pulp is edematous, hyperemic, and bright red in color. Small hemorrhages may be found around the vessels. Purulent exudate is initially found as a local accumulation, then spreads to the entire crown and root pulp acquiring a grayish-red or gray appearance.
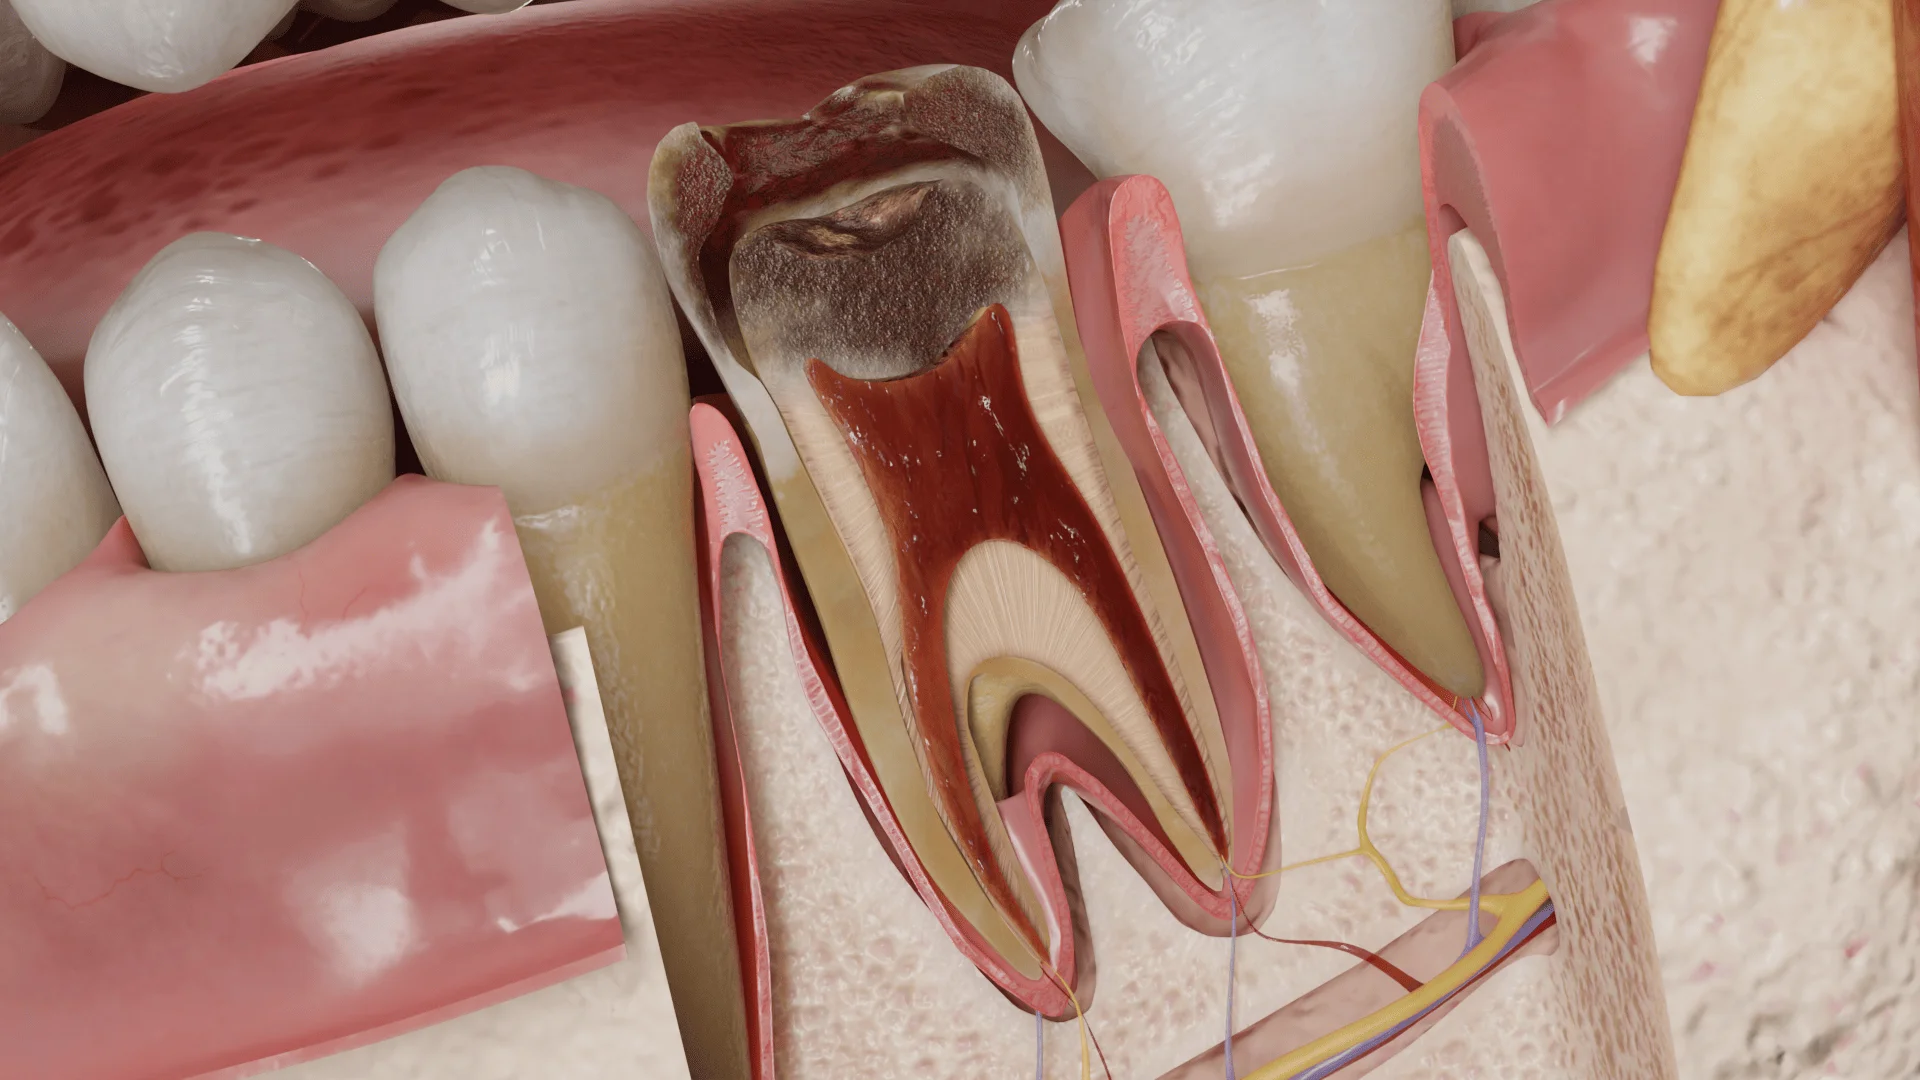
In a chronic process, the pulp is replaced by granulation tissue, and then by dense, coarse fibrous scar tissue of a whitish color.
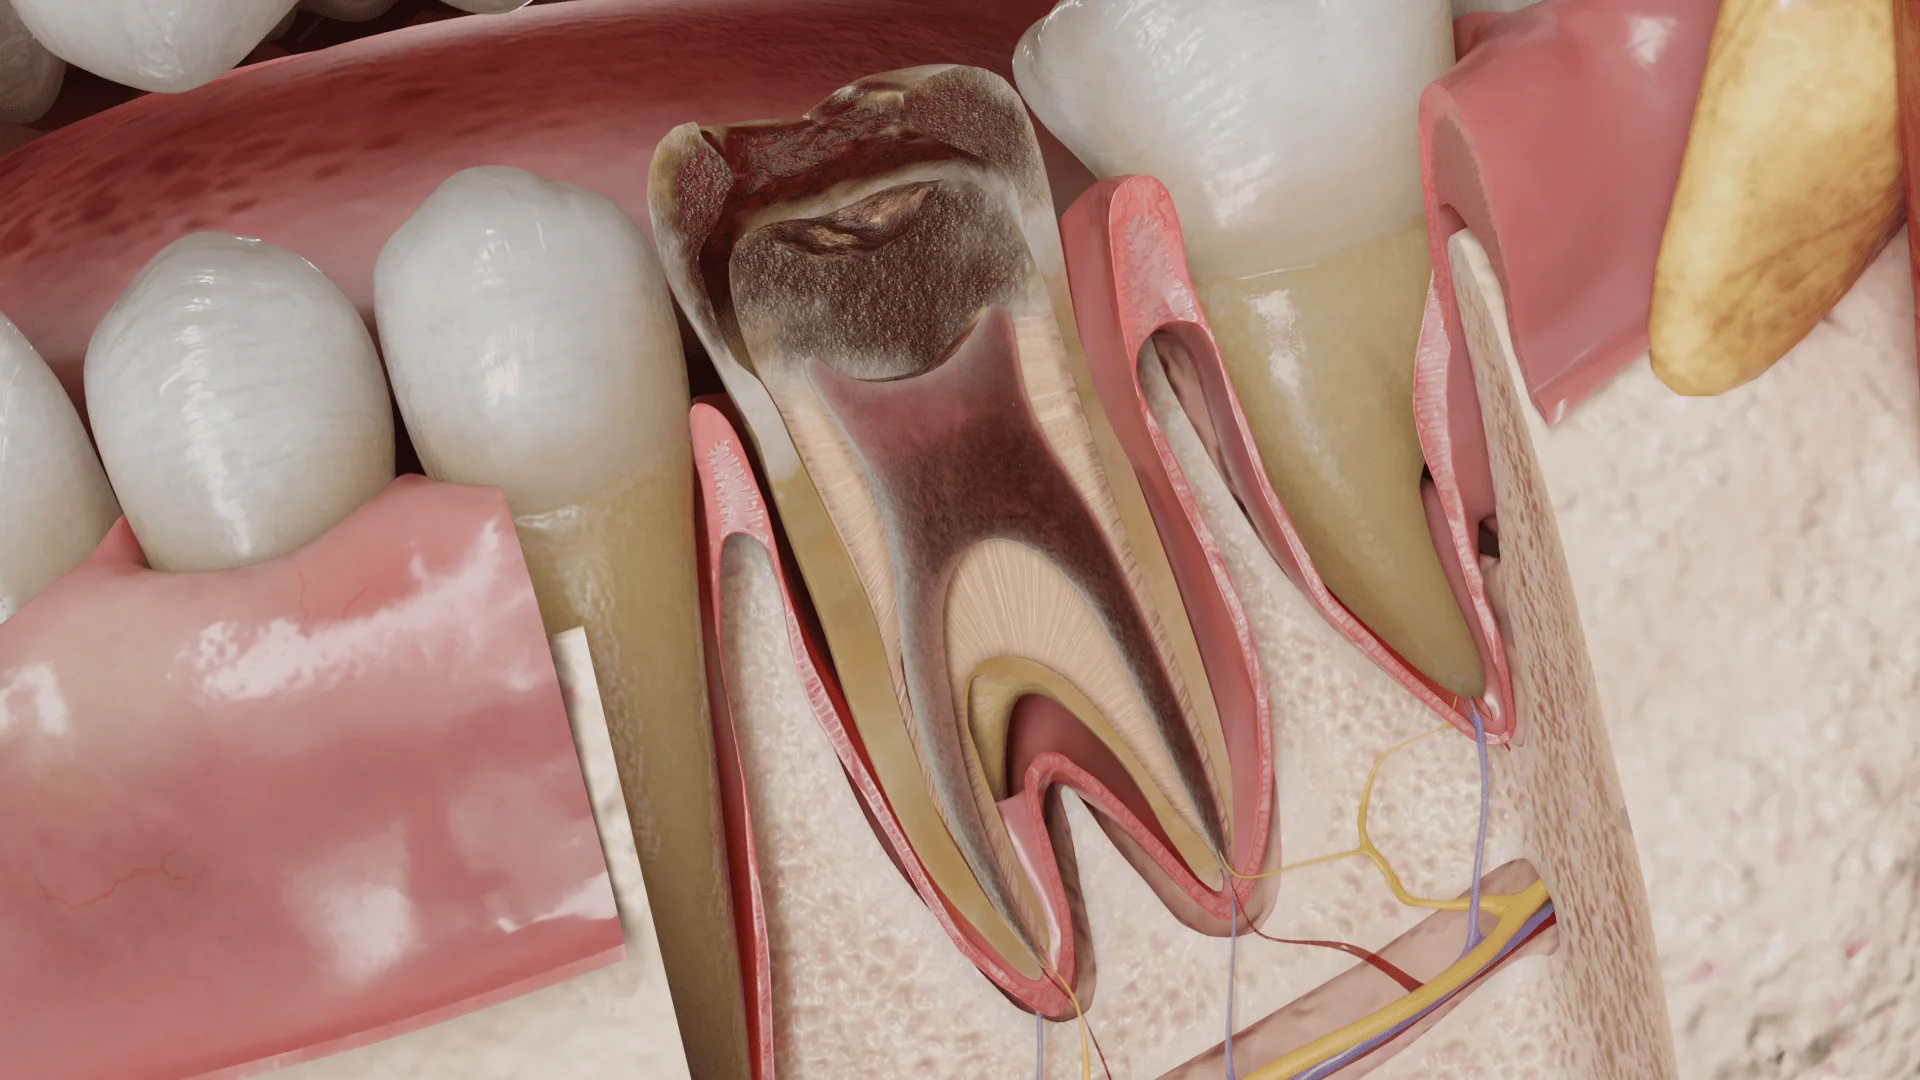
In acute pulpitis, the patient complains of ‘spontaneous’ paroxysmal pain – a sensation that occurs spontaneously regardless of external stimuli. The frequency and duration of pain attacks and ‘light’ pain-free intervals change over time. Initially, short episodes of pain (from a few minutes to a few hours) alternate with prolonged pain-free intervals (from a few hours to a few days). As the process progresses, the frequency and duration of pain attacks increase. Pain often occurs at night. The nature of the pain is dull, aching, excruciating, prolonged, sometimes sharp and throbbing, can reach considerable intensity and become unbearable. This pain frequently radiates to adjacent teeth or antagonists and may migrate.
Exposure to thermal, mechanical, and chemical stimuli leads to prolonged pain episodes that persist even after the irritant is removed.
Chronic pulpitis is characterized by a discrepancy between the weak expression of the pain symptom and the significant degree of tooth destruction. The patient complains of prolonged pain arising from the action of irritants, while spontaneous and nocturnal pain are usually absent.
Find more scientifically accurate content on our social media


Acute irreversible pulpitis accompanied by spontaneous pain is an emergency requiring immediate treatment.
Endodontic treatment: involves complete removal of the pulp, mechanical and medicinal treatment of root canals, and their hermetic obturation followed by tooth restoration.
In permanent teeth with incomplete root formation, revascularization and apexogenesis techniques may be possible.
If the prognosis of endodontic treatment is unsatisfactory, the tooth should be extracted.
1. What is irreversible pulpitis?
2. What causes irreversible pulpitis?
3. What are the symptoms of acute irreversible pulpitis?
4. What are the signs of chronic irreversible pulpitis?
5. How is irreversible pulpitis treated?
6. Can irreversible pulpitis be treated without pulp removal?
References
1.
VOKA 3D Anatomy & Pathology – Complete Anatomy and Pathology 3D Atlas. VOKA 3D Anatomy & Pathology.
Available from: https://catalog.voka.io/
2.
Berman LH, Hargreaves KM, editors. Cohen’s pathways of the pulp expert consult. 12th ed. S. Louis (MO): Elsevier; 2020.
3.
Jain N, Gupta A, N M. An insight into neurophysiology of pulpal pain: facts and hypotheses. Korean J Pain. 2013 Oct;26(4):347-55. doi: 10.3344/kjp.2013.26.4.347.
4.
Torabinejad M, Fouad A, Shabahang S, editors. Endodontics: principles and practice. 6th ed. S. Louis (MO): Elsevier; 2020.
5.
American Association of Endodontists. Guide to clinical endodontics [Internet]. Chicago: American Association of Endodontists; 2019 Jun 3.
Available from: https://www.aae.org/specialty/clinical-resources/guide-clinical-endodontics/
6.
Ricucci D, Siqueira JF. Endodontology: an integrated biological and clinical view. Hanover Park (IL): Quintessence Publishing; 2013.
7.
Bergenholtz G, Hørsted-Bindslev P, Reit C, editors. Textbook of endodontology. 2nd ed. Chichester (UK): Wiley-Blackwell; 2013.
8.
Hülsmann M, Schäfer E, Bargholz C, Barthel C. Problems in endodontics: etiology, diagnosis and treatment. Hanover Park (IL): Quintessence Publishing; 2009.
9.
Beer R, Baumann MA, Kielbassa AM. Taschenatlas der Endodontie [Pocket atlas of endodontics]. Stuttgart: Georg Thieme Verlag; 2004. German
Make VOKA your preferred source
See more VOKA articles in Google Search
Table of Contents








Summarize article with AI
Choose your preferable AI assistant:
Link successfully copied to clipboard
Thank you!
Your message is sent!
Our experts will contact you shortly. If you have any additional questions, please contact us at info@voka.io